
What is physiological assessment of a coronary artery?
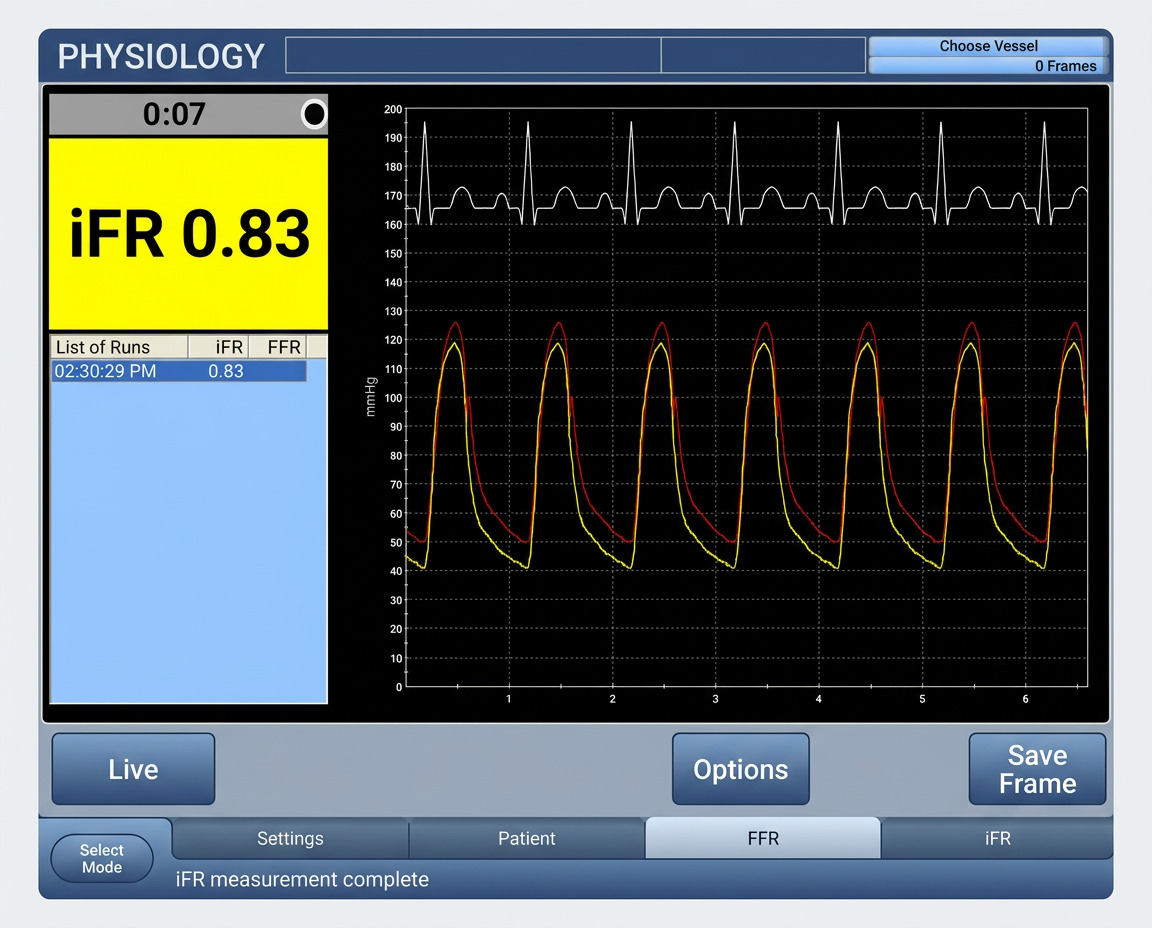
An angiogram shows a picture of a narrowing, but a picture alone cannot always tell whether that narrowing is actually starving the heart muscle of blood. Physiological assessment measures this directly. A very fine pressure-sensing wire is passed down the artery and the pressure beyond the narrowing is compared with the pressure before it. The result is given as a number, such as FFR or iFR, which tells your cardiologist whether the narrowing is significant or not.
Why is it done?
It answers a practical question: does this narrowing need a stent? If the number shows that blood flow is not meaningfully limited, medication alone is the better treatment and an unnecessary stent, with its lifelong implications, is avoided. If the number shows that flow is restricted, stenting relieves symptoms and improves the outcome. Guiding treatment with these measurements has been shown in large studies to lead to fewer stents, fewer complications and better results, and it is especially useful for borderline narrowings and where several arteries are involved.
What happens on the day?
The measurement is made during your angiogram, so there is no separate appointment. You are awake and comfortable, with the wrist or groin numbed with local anaesthetic. The pressure wire is advanced through the catheter into the artery and past the narrowing. For an FFR measurement a medicine is given, either through the drip or into the artery, to make the small vessels of the heart open up fully; this can cause a few seconds to a couple of minutes of chest heaviness, breathlessness or a flushed, uncomfortable feeling that passes as soon as the medicine is stopped. For an iFR measurement no such medicine is needed. The whole step adds only a few minutes.
What to expect afterwards
There is no separate recovery: your aftercare is that of the angiogram, with a compression band on the wrist for a few hours or a period lying flat if the groin was used. Any sensation caused by the medicine disappears almost immediately. Your cardiologist will explain the numbers and what they mean, and if a stent is indicated it is often placed in the same sitting and the measurement repeated afterwards to confirm a good result.
Possible complications
The added risk is small. The medicine used for FFR commonly causes temporary chest discomfort, breathlessness, flushing or a slow heartbeat, all of which settle within seconds of stopping it; it is avoided in patients with significant asthma. Passing the wire can, uncommonly, cause spasm of the artery, a small tear of the vessel wall or a disturbance of rhythm, and very rarely a clot or perforation, which are treated immediately in the laboratory. The remaining risks are those of the angiogram itself, which your cardiologist will discuss with you.
This information does not replace a consultation. Please discuss your own risks and options with your cardiologist.